
Sat, Sep 19, 2026

Volume 20, Issue 2 (Mar-Apr 2026)
mljgoums 2026, 20(2): 11-15 |
Back to browse issues page


Download citation:
BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:


BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:
Okey-kalu E U, Okoli I, Nwankwo E O. Detection of the mecA gene and methicillin-resistant Staphylococcus aureus isolated from inanimate surfaces and healthcare workers in tertiary hospitals in Abia state, Nigeria. mljgoums 2026; 20 (2) :11-15
URL: http://mlj.goums.ac.ir/article-1-1930-en.html
URL: http://mlj.goums.ac.ir/article-1-1930-en.html


1- Department of Applied Microbiology and Brewing, Faculty of Biosciences, Nnamdi Azikiwe University, Awka, Anambra state, Nigeria , ulomamgbeokwere@yahoo.com
2- Department of Applied Microbiology and Brewing, Faculty of Biosciences, Nnamdi Azikiwe University, Awka, Anambra state, Nigeria
3- Department of Microbiology, College of Natural sciences, Michael Okpara University of Agriculture, Umudike, Abia state, Nigeria
2- Department of Applied Microbiology and Brewing, Faculty of Biosciences, Nnamdi Azikiwe University, Awka, Anambra state, Nigeria
3- Department of Microbiology, College of Natural sciences, Michael Okpara University of Agriculture, Umudike, Abia state, Nigeria
Keywords: Staphylococcus aureus, Methicillin-Resistant Staphylococcus Aureus, Healthcare Workers, Inanimate Surfaces
Full-Text [PDF 441 kb]
(1902 Downloads)
| Abstract (HTML) (6942 Views)
When the prevalence of S. aureus on inanimate surfaces and among healthcare workers was compared, healthcare workers had a higher percentage (68.85%) than inanimate surfaces (45.69%).
The antibiotic susceptibility profile of S. aureus isolates is provided in Table 3. The isolates were more susceptible to meropenem, augmentin, tetracycline, ceftazidime, cefuroxime, and cephalexin. Of the 206 S. aureus isolates tested for MRSA using cefoxitin disk diffusion, 43.69% (n = 90) were methicillin-resistant (Table 4).
Discussion
S. aureus (45.69%) was the prevalent bacterium isolated from inanimate surfaces/fomites in this study. These results are comparable to those of the Brazilian study, which found that S. aureus was the primary organism isolated from fomites 53.3 percent of the time (25). The findings of Munveshyaka et al. (26) on inanimate surfaces and equipment are also consistent with these findings. S. aureus can form biofilms on inanimate surfaces/fomites, and these biofilms can be more resistant to disinfectants and cleaning efforts, making them a more persistent source of infection.
S. aureus was observed more frequently in the nostrils than on the palms of the hands in this study, which corresponds to the findings of Pant and Sharma (27) and Junu et al. (28). This result is consistent with the notion that S. aureus most frequently colonizes the nostrils. Compared with nasal carriers, there are fewer reports of hand carriers. Compared with Mukhiya et al. (29) and Pant and Sharma (27), the prevalence of palm-of-hand carriers was lower, which may suggest that the healthcare workers who took part in this study practiced better hand hygiene. In this investigation, every hand carrier was also a nasal carrier, and the isolates from both locations shared similar antibiograms, indicating that they were phenotypically identical. The notion that hands are the primary vector for spreading S. aureus from surfaces to the nostrils and from the nostrils to surfaces is further supported by the possibility that these carriers tend to pick their noses.
The bacterial isolates were resistant to frequently used antibiotics. Erythromycin (29.13%), cotrimoxazole (29.13%), gentamicin (33.98%), ampicillin (33.98%), and ciprofloxacin (36.41%) had low susceptibility rates against S. aureus. S. aureus was more resistant to these drugs. This could be due to their availability, cost, and misuse. This is in line with the findings of Sanusi et al. (30). Adam et al. (31), on the other hand, found that the highest rate of S. aureus resistance was to trimethoprim-sulfamethoxazole. This could be due to the development of resistance mechanisms such as reduced antibiotic accumulation within the bacteria and bypassing the antibiotic's inhibitory effects.
Of the 390 bacterial isolates obtained from the two tertiary hospitals in Abia State, 206 (52.82%) were positive for S. aureus. Mukhiya et al. (32) and Firesbhat et al. (33) reported the presence of S. aureus on hospital surfaces in Nepal and Ethiopia, respectively, despite the scarcity of data regarding the prevalence of MRSA in Nigeria. These results contradict those of this investigation. The findings of this study are in line with those of Anyadoh et al. (34) and Sanusi et al. (30), who found that more than 50% of hospital surfaces were contaminated with S. aureus.
The rise of MRSA, which is resistant to cephalosporins, a class of antibiotics commonly used to treat Staphylococcus infections, as well as monobactams and all beta-lactam drugs, has worsened the emergence of S. aureus infections (35). Identifying MRSA accurately requires prompt and early diagnosis because MRSA infections lead to treatment issues and spread (36).
In this study, 90 (43.69%) S. aureus isolates were found to be resistant by the cefoxitin disk diffusion test for MRSA. This is comparable to the study by Khairullah et al. (37), which revealed that 47.62% of the isolates tested positive for MRSA. In comparison, Adam et al. (31) and Oguzkaya-Artan et al. (38) reported 2.1% of MRSA positivity, while Sanusi et al. (30) reported 5.4%. According to this study, a number of variables, such as improper hand hygiene and failure to clean surfaces, might contribute to the development of MRSA contamination on fomites/inanimate surfaces and healthcare personnel. MRSA contamination raises the possibility of the spread of hard-to-treat Staphylococci, posing a major public health danger.
According to Miragaia (39), mecA genotyping by PCR remains the primary recommendation despite its inability to be carried out on a regular basis, and phenotypic detection of MRSA via disk diffusion has not yet yielded fully reliable results. Nevertheless, because of its speed and affordability, disk diffusion identification of MRSA is still often utilized (40).
Oxacillin and cefoxitin diffusion disks exhibit the same 100% sensitivity and 74.07% and 92.59% specificities, respectively (41). However, because there is still a high percentage of false positives with the oxacillin disk diffusion approach, a number of earlier investigations found that cefoxitin disk diffusion had a higher sensitivity level than oxacillin for identifying MRSA (42). According to Vyas et al. (41), beta-lactamase hyperproduction may contribute to false positives by causing oxacillin resistance to manifest phenotypically without a genotypic resistance mechanism.
A total of 20 suspected methicillin-resistant S. aureus isolates were tested for the mecA gene, and only 4 isolates (20% of all isolates tested by PCR) were mecA gene-positive. This might be due to false positives in the phenotypic analysis. Suspected MRSA isolates were found to have the mecA gene, as shown by the PCR results. This is similar to Khirullah et al. (37), where 30% of the MRSA isolates tested were mecA gene-positive. However, this contrasts with Sanusi et al. (30), who reported that 83.33% of MRSA isolates were positive for the mecA gene. These findings are in line with the study by Ramandinianto et al. (43). Because it can increase the expression of PBP2a, which the mecA gene encodes, cefoxitin is an effective inducer of mecA gene expression (44). This also agrees with Reichmann and Pinho (45).
Conclusion
This study was conducted to detect the mecA gene and MRSA from S. aureus isolated from inanimate surfaces, palms of the hands, and nostrils of healthcare workers in selected hospital wards in the two tertiary hospitals in Abia State. This study found an MRSA prevalence of 43.69% and mecA gene positivity of only 20%.
The hospital wards evaluated in this study showed the presence of bacterial pathogens on inanimate surfaces and in the nostrils of healthcare workers, with S. aureus being the prevalent bacterial isolate in this study. Nasal carriage was higher than hand carriage in this study.
The presence of MRSA in the two tertiary hospitals poses a risk to healthcare and community environments by contaminating healthcare workers, patients, visitors, and surrounding surfaces. This could ultimately lead to community exposure to resistant bacteria. Therefore, prevention and control measures are required to stop the spread of S. aureus infections on fomites/inanimate surfaces and among healthcare personnel at tertiary hospitals in Abia State.
However, the unavailability of molecular laboratories in close proximity to run the mecA gene analysis immediately limited this study.
Acknowledgement
We thank the management of the Federal Medical Centre, Umuahia, and the Abia State University Teaching Hospital, Aba, Abia State, for granting ethical approval. We are grateful to the healthcare workers who participated in this study for their informed consent. We also acknowledge Sir and Lady O. Mgbeokwere for their financial support.
Funding Sources
Not applicable.
Ethical Statement
The ethics committees of the Federal Medical Centre, Umuahia (Code: FMC/QEH/G.596/Vol.10/746), and Abia State University Teaching Hospital (Code: ABSUTH/MAC/117/VOL1/60) approved the study.
Conflicts of Interest
The authors have no competing interests.
Author Contributions
EUO: Conceptualization; Methodology; Data curation; Formal analysis; Funding acquisition; Investigation; Resources; Visualization; Writing-Original draft; Writing-Review and Editing. IO: Supervision; Methodology. EON: Methodology; Investigation; Interpretation.
Data Availability Statement
All data are available upon request from the corresponding author.
Use of Artificial Intelligence
The authors declare that no artificial intelligence tools were used in this work.
Full-Text: (899 Views)
Introduction
Infections acquired in hospitals or other healthcare facilities are a significant public health issue (1). In developed nations, the prevalence of healthcare-associated infections (HAIs) is already high, affecting between 5% and 15% of patients admitted to standard wards and up to 50% of critically ill patients in intensive care units (ICUs) (2,3).
It is obvious that monitoring the hospital environment is crucial for preventing nosocomial infections. Although hand-to-hand contact is likely the greatest risk, surface contamination may also serve as a potential source of infection. Multidrug-resistant (MDR) microorganisms may contaminate high-contact communal items, such as telephones and medical charts, as well as the surfaces of frequently used medical equipment, necessitating laborious, expensive, and complicated operations to improve patient safety (4,5). The problem of environmental contamination presents an even greater challenge in the intensive care unit (ICU), where critically ill patients have multiple risk factors for nosocomial infections (6).
This issue becomes especially significant when multiresistant bacteria, such as non-fermenting rods, methicillin-resistant Staphylococcus, and vancomycin-resistant enterococci, arise in hospital settings (7-9).
MRSA, methicillin-resistant S. aureus, is among the most prevalent bacterial strains causing hard-to-control infections in hospital settings (10).
Coagulase-positive staphylococci (Such as S. aureus) and coagulase-negative staphylococci (S. epidermidis and S. saprophyticus) are germs that readily contaminate the hospital environment. People with venous catheters, individuals with diabetes, and healthcare workers are more susceptible to S. aureus. However, methicillin-resistant S. aureus (MRSA) poses the greatest threat because it causes nosocomial infections with exceptionally high rates of morbidity and mortality (11). S. aureus was one of the frequently isolated pathogens between 2006 and 2007 linked to nosocomial infections reported to the National Healthcare Safety Network. Of hospital supplies and equipment contaminated with S. aureus, 56% involved MRSA. Colonized or infected individuals are the most significant source of MRSA in hospitals because they can readily contaminate nearby electronic and medical equipment. MRSA can persist on dry surfaces for several months (12,13). Although the contaminated hands of healthcare workers are the main route by which MRSA is spread to patients, evidence indicates that patient infections can also result from exposure to MRSA-contaminated surfaces (14,15).
According to evidence from the literature review, S. aureus can survive on dry surfaces for anywhere from one week to three years (16). Although there is evidence that S. aureus may survive in both home and clinical environments, the dissemination of these organisms, especially MRSA, across the population has received less attention (17). According to certain studies, S. aureus may survive on a wide range of inanimate surfaces, including polyethylene for 90 days, sterile packaging for 266 days, screw-cap bottles for 318 days, and polypropylene for more than 1097 days (18). However, these results appear to be based on optimization of the experimental setup. These studies employed an inoculum of 107-109 CFU and staphylococcal strains that were highly resistant to desiccation. Although these findings were clear and consistent in the laboratory, they may not truly represent S. aureus survival in the general population. Because of their limited survival on dry surfaces for longer than 24 hours, dangerous and pathogenic S. aureus strains, such as MRSA, which cause hospital-associated infections, are rarely isolated from environmental fomites (19).
The epidemiology of MRSA, particularly on inanimate surfaces, has remained understudied in Abia State, Nigeria, and this may have contributed to its increase in hospital-acquired infections. The main aim of this study was to detect MRSA among S. aureus isolates and to detect the presence of the mecA gene among selected MRSA isolates.
This study was necessary because the majority of isolates recovered from inanimate surfaces, nostrils, and palms of the hands of healthcare workers in tertiary hospitals in Abia State were S. aureus.
Methods
This cross-sectional study was carried out in selected hospital wards in Federal Medical Centre, Umuahia, and Abia State University Teaching Hospital, Aba. Ethical approval was obtained from the healthcare facilities before sampling and analysis. Informed consent was obtained from the participating healthcare workers with utmost confidentiality.
The present study focused on 206 S. aureus isolates collected from inanimate surfaces, palms of the hands, and nostrils of healthcare workers after laboratory analysis. One hundred and twenty-two S. aureus isolates were collected from inanimate surfaces, while 84 S. aureus isolates were collected from the palms of the hands and nostrils of healthcare workers. A total of 14 S. aureus isolates were collected from the palms of the hands, while 70 S. aureus isolates were collected from nostrils. Sterile swab sticks dampened with sterile water were used to swab the surfaces of mattresses, tables, footwear, clinical coats, bed sheets, and pillows. These inanimate surfaces were selected based on their frequent use and direct contact with patients, healthcare workers, and visitors. Sterile swab sticks dampened with sterile water were used to swab the palms of the hands of healthcare workers, and sterile swab sticks were used to swab the nostrils of healthcare workers. To ensure that each surface area was well covered, the swab sticks were rotated.
Gram-stained isolates were identified using standard biochemical tests after the swab sticks were inoculated onto appropriate media (Blood agar and mannitol salt agar) and incubated for 24 to 48 hours at 37°C. Pigment production, acid production, coagulase, and catalase tests were the biochemical tests used to confirm S. aureus isolates from mannitol salt agar (20).
The disk diffusion method was used to test antibiotic susceptibility, and the results were interpreted in accordance with Clinical Laboratory Standards Institute guidelines (21). Sterile cotton wool swabs were dipped into a suspension of the organism's overnight growth prepared to the density of a 0.5 McFarland opacity standard to inoculate Mueller-Hinton culture plates. Any excess liquid from the swab was then expressed using the spread plate procedure before inoculation.
The antibiotic disks (Biomark, India) used had the following concentrations: tetracycline, 30 µg; ampicillin, 10 µg; meropenem, 10 µg; gentamicin, 10 µg; erythromycin, 5 µg; ciprofloxacin, 5 µg; cotrimoxazole, 25 µg; cefuroxime, 10 µg; augmentin, 30 µg; cefalexin, 10 µg; vancomycin, 30 µg; ceftazidime, 10 µg; chloramphenicol, 10 µg; ceftriaxone, 30 µg; cefotaxime, 30 µg; and amikacin, 30 µg.
To ensure that the growth was confluent or near confluent, the control and test plates were examined after overnight incubation. The diameter of each zone of inhibition was measured in mm using a ruler on the underside of the plate. Growth began at the endpoint of inhibition (22).
The Clinical and Laboratory Standards Institute criteria (23) were followed when conducting the test. Each isolate was suspended to a turbidity of 0.5 McFarland standard before being plated onto a Mueller-Hinton agar plate (Hardy Diagnostics, USA). On each plate, a 30 µg cefoxitin disk (Oxoid) was placed. Zone sizes were assessed after a 24-hour incubation period at 35°C. Resistance was defined as an inhibitory zone size of less than or equal to 19 mm. ATCC 33591 (MRSA) and ATCC 29213 (MSSA) were used as control strains.
To provide a detailed explanation, each isolate was cultured in 1 mL of sterile water in different 1.5 mL microcentrifuge tubes. For one minute, the samples were centrifuged at 10,000 rpm, and the supernatants were discarded.
After adding 200 µL of lysis buffer to each tube containing the pelleted samples, a vortex mixer was used to mix it thoroughly for a few seconds. The samples were incubated in a heating block machine (Biobase) at 55°C for 10 minutes. The samples were allowed to cool after incubation and were then centrifuged at 10,000 rpm for 30 seconds.
After this step, 200 µL of absolute ethanol was added to each sample, and the supernatants were carefully transferred into well-labeled spin columns fitted into collection tubes without dislodging the pellets.
The spin columns were centrifuged at 10,000 rpm for 1 minute, and the flow collected in the collection tubes was discarded.
Using 500 µL of wash buffer 1 and 2, respectively, the DNA trapped on the silica membrane in the spin columns was washed.
At each washing stage, the spin columns were centrifuged at 10,000 rpm for 30 seconds to allow the wash buffer to pass into the collection tubes.
To remove any traces of ethanol, the spin columns were spin-dried at 14,000 rpm. DNA samples were eluted into well-labeled, nuclease-free 1.5 mL microcentrifuge tubes with 50 µL of elution buffer. After elution, the DNA samples were stored at -20°C until further analysis (24).
The mecA gene was amplified by polymerase chain reaction (PCR) using specific primer pairs (mecA-F: 5'-AAAATCGATGGTAAAGGTTGGC-3'; mecA-R: 5'-AGTTCTGCAGTA CCGGATTTGC-3') (24).
For each isolate's DNA samples, a total reaction volume of 25 µL was prepared using 5X HOT FIREPol Blend Master Mix with 7.5 mM MgCl2 (Solis Biodyne). This was diluted to 1X concentration using 1X Blend Master Mix buffer (Solis Biodyne), 1.5 mM MgCl2, 200 µM of each deoxynucleoside triphosphate (dNTP) (Solis Biodyne), 25 pMol of each forward and reverse primer (BIOMERS, Germany), 2 units of Hot FIREPol DNA polymerase (Solis Biodyne), proofreading enzyme, 5 µL of extracted DNA, and sterile distilled water.
After five minutes of initial denaturation at 95°C, 30 amplification cycles of 30 seconds at 95°C, 30 seconds at 58°C, and 45 seconds at 72°C were carried out using a PTC 200 gradient thermal cycler Eppendorf. A final extension phase of 10 minutes at 72°C followed. Electrophoresis was performed at 80 V for 60 minutes after the resultant amplicons were separated on a 1.5% agarose gel. After electrophoresis, ethidium bromide staining and a UV transilluminator were used to view the DNA bands. A 100 bp DNA ladder was used as the DNA molecular weight marker (24).
Statistical analysis
SPSS statistical software version 20.0 was used for data analysis. Categorical variables, such as the frequency of the bacterial isolates, were summarized using proportions expressed as percentages.
Results
The prevalence of S. aureus on inanimate surfaces is provided in Table 1. Of the 122 S. aureus isolates collected from inanimate surfaces, footwear harbored the highest proportion (39.34%, n = 48), followed by mattresses (38.52%, n = 47), while clinical coats had the lowest proportion (0.82%, n = 1). At a 95% confidence level, the calculated t-test value (4.366) was greater than the critical t-test value (2.015), indicating that the result was statistically significant and unlikely to be due to random chance.
Infections acquired in hospitals or other healthcare facilities are a significant public health issue (1). In developed nations, the prevalence of healthcare-associated infections (HAIs) is already high, affecting between 5% and 15% of patients admitted to standard wards and up to 50% of critically ill patients in intensive care units (ICUs) (2,3).
It is obvious that monitoring the hospital environment is crucial for preventing nosocomial infections. Although hand-to-hand contact is likely the greatest risk, surface contamination may also serve as a potential source of infection. Multidrug-resistant (MDR) microorganisms may contaminate high-contact communal items, such as telephones and medical charts, as well as the surfaces of frequently used medical equipment, necessitating laborious, expensive, and complicated operations to improve patient safety (4,5). The problem of environmental contamination presents an even greater challenge in the intensive care unit (ICU), where critically ill patients have multiple risk factors for nosocomial infections (6).
This issue becomes especially significant when multiresistant bacteria, such as non-fermenting rods, methicillin-resistant Staphylococcus, and vancomycin-resistant enterococci, arise in hospital settings (7-9).
MRSA, methicillin-resistant S. aureus, is among the most prevalent bacterial strains causing hard-to-control infections in hospital settings (10).
Coagulase-positive staphylococci (Such as S. aureus) and coagulase-negative staphylococci (S. epidermidis and S. saprophyticus) are germs that readily contaminate the hospital environment. People with venous catheters, individuals with diabetes, and healthcare workers are more susceptible to S. aureus. However, methicillin-resistant S. aureus (MRSA) poses the greatest threat because it causes nosocomial infections with exceptionally high rates of morbidity and mortality (11). S. aureus was one of the frequently isolated pathogens between 2006 and 2007 linked to nosocomial infections reported to the National Healthcare Safety Network. Of hospital supplies and equipment contaminated with S. aureus, 56% involved MRSA. Colonized or infected individuals are the most significant source of MRSA in hospitals because they can readily contaminate nearby electronic and medical equipment. MRSA can persist on dry surfaces for several months (12,13). Although the contaminated hands of healthcare workers are the main route by which MRSA is spread to patients, evidence indicates that patient infections can also result from exposure to MRSA-contaminated surfaces (14,15).
According to evidence from the literature review, S. aureus can survive on dry surfaces for anywhere from one week to three years (16). Although there is evidence that S. aureus may survive in both home and clinical environments, the dissemination of these organisms, especially MRSA, across the population has received less attention (17). According to certain studies, S. aureus may survive on a wide range of inanimate surfaces, including polyethylene for 90 days, sterile packaging for 266 days, screw-cap bottles for 318 days, and polypropylene for more than 1097 days (18). However, these results appear to be based on optimization of the experimental setup. These studies employed an inoculum of 107-109 CFU and staphylococcal strains that were highly resistant to desiccation. Although these findings were clear and consistent in the laboratory, they may not truly represent S. aureus survival in the general population. Because of their limited survival on dry surfaces for longer than 24 hours, dangerous and pathogenic S. aureus strains, such as MRSA, which cause hospital-associated infections, are rarely isolated from environmental fomites (19).
The epidemiology of MRSA, particularly on inanimate surfaces, has remained understudied in Abia State, Nigeria, and this may have contributed to its increase in hospital-acquired infections. The main aim of this study was to detect MRSA among S. aureus isolates and to detect the presence of the mecA gene among selected MRSA isolates.
This study was necessary because the majority of isolates recovered from inanimate surfaces, nostrils, and palms of the hands of healthcare workers in tertiary hospitals in Abia State were S. aureus.
Methods
This cross-sectional study was carried out in selected hospital wards in Federal Medical Centre, Umuahia, and Abia State University Teaching Hospital, Aba. Ethical approval was obtained from the healthcare facilities before sampling and analysis. Informed consent was obtained from the participating healthcare workers with utmost confidentiality.
The present study focused on 206 S. aureus isolates collected from inanimate surfaces, palms of the hands, and nostrils of healthcare workers after laboratory analysis. One hundred and twenty-two S. aureus isolates were collected from inanimate surfaces, while 84 S. aureus isolates were collected from the palms of the hands and nostrils of healthcare workers. A total of 14 S. aureus isolates were collected from the palms of the hands, while 70 S. aureus isolates were collected from nostrils. Sterile swab sticks dampened with sterile water were used to swab the surfaces of mattresses, tables, footwear, clinical coats, bed sheets, and pillows. These inanimate surfaces were selected based on their frequent use and direct contact with patients, healthcare workers, and visitors. Sterile swab sticks dampened with sterile water were used to swab the palms of the hands of healthcare workers, and sterile swab sticks were used to swab the nostrils of healthcare workers. To ensure that each surface area was well covered, the swab sticks were rotated.
Gram-stained isolates were identified using standard biochemical tests after the swab sticks were inoculated onto appropriate media (Blood agar and mannitol salt agar) and incubated for 24 to 48 hours at 37°C. Pigment production, acid production, coagulase, and catalase tests were the biochemical tests used to confirm S. aureus isolates from mannitol salt agar (20).
The disk diffusion method was used to test antibiotic susceptibility, and the results were interpreted in accordance with Clinical Laboratory Standards Institute guidelines (21). Sterile cotton wool swabs were dipped into a suspension of the organism's overnight growth prepared to the density of a 0.5 McFarland opacity standard to inoculate Mueller-Hinton culture plates. Any excess liquid from the swab was then expressed using the spread plate procedure before inoculation.
The antibiotic disks (Biomark, India) used had the following concentrations: tetracycline, 30 µg; ampicillin, 10 µg; meropenem, 10 µg; gentamicin, 10 µg; erythromycin, 5 µg; ciprofloxacin, 5 µg; cotrimoxazole, 25 µg; cefuroxime, 10 µg; augmentin, 30 µg; cefalexin, 10 µg; vancomycin, 30 µg; ceftazidime, 10 µg; chloramphenicol, 10 µg; ceftriaxone, 30 µg; cefotaxime, 30 µg; and amikacin, 30 µg.
To ensure that the growth was confluent or near confluent, the control and test plates were examined after overnight incubation. The diameter of each zone of inhibition was measured in mm using a ruler on the underside of the plate. Growth began at the endpoint of inhibition (22).
The Clinical and Laboratory Standards Institute criteria (23) were followed when conducting the test. Each isolate was suspended to a turbidity of 0.5 McFarland standard before being plated onto a Mueller-Hinton agar plate (Hardy Diagnostics, USA). On each plate, a 30 µg cefoxitin disk (Oxoid) was placed. Zone sizes were assessed after a 24-hour incubation period at 35°C. Resistance was defined as an inhibitory zone size of less than or equal to 19 mm. ATCC 33591 (MRSA) and ATCC 29213 (MSSA) were used as control strains.
To provide a detailed explanation, each isolate was cultured in 1 mL of sterile water in different 1.5 mL microcentrifuge tubes. For one minute, the samples were centrifuged at 10,000 rpm, and the supernatants were discarded.
After adding 200 µL of lysis buffer to each tube containing the pelleted samples, a vortex mixer was used to mix it thoroughly for a few seconds. The samples were incubated in a heating block machine (Biobase) at 55°C for 10 minutes. The samples were allowed to cool after incubation and were then centrifuged at 10,000 rpm for 30 seconds.
After this step, 200 µL of absolute ethanol was added to each sample, and the supernatants were carefully transferred into well-labeled spin columns fitted into collection tubes without dislodging the pellets.
The spin columns were centrifuged at 10,000 rpm for 1 minute, and the flow collected in the collection tubes was discarded.
Using 500 µL of wash buffer 1 and 2, respectively, the DNA trapped on the silica membrane in the spin columns was washed.
At each washing stage, the spin columns were centrifuged at 10,000 rpm for 30 seconds to allow the wash buffer to pass into the collection tubes.
To remove any traces of ethanol, the spin columns were spin-dried at 14,000 rpm. DNA samples were eluted into well-labeled, nuclease-free 1.5 mL microcentrifuge tubes with 50 µL of elution buffer. After elution, the DNA samples were stored at -20°C until further analysis (24).
The mecA gene was amplified by polymerase chain reaction (PCR) using specific primer pairs (mecA-F: 5'-AAAATCGATGGTAAAGGTTGGC-3'; mecA-R: 5'-AGTTCTGCAGTA CCGGATTTGC-3') (24).
For each isolate's DNA samples, a total reaction volume of 25 µL was prepared using 5X HOT FIREPol Blend Master Mix with 7.5 mM MgCl2 (Solis Biodyne). This was diluted to 1X concentration using 1X Blend Master Mix buffer (Solis Biodyne), 1.5 mM MgCl2, 200 µM of each deoxynucleoside triphosphate (dNTP) (Solis Biodyne), 25 pMol of each forward and reverse primer (BIOMERS, Germany), 2 units of Hot FIREPol DNA polymerase (Solis Biodyne), proofreading enzyme, 5 µL of extracted DNA, and sterile distilled water.
After five minutes of initial denaturation at 95°C, 30 amplification cycles of 30 seconds at 95°C, 30 seconds at 58°C, and 45 seconds at 72°C were carried out using a PTC 200 gradient thermal cycler Eppendorf. A final extension phase of 10 minutes at 72°C followed. Electrophoresis was performed at 80 V for 60 minutes after the resultant amplicons were separated on a 1.5% agarose gel. After electrophoresis, ethidium bromide staining and a UV transilluminator were used to view the DNA bands. A 100 bp DNA ladder was used as the DNA molecular weight marker (24).
Statistical analysis
SPSS statistical software version 20.0 was used for data analysis. Categorical variables, such as the frequency of the bacterial isolates, were summarized using proportions expressed as percentages.
Results
The prevalence of S. aureus on inanimate surfaces is provided in Table 1. Of the 122 S. aureus isolates collected from inanimate surfaces, footwear harbored the highest proportion (39.34%, n = 48), followed by mattresses (38.52%, n = 47), while clinical coats had the lowest proportion (0.82%, n = 1). At a 95% confidence level, the calculated t-test value (4.366) was greater than the critical t-test value (2.015), indicating that the result was statistically significant and unlikely to be due to random chance.
|
Table 1. Prevalence of Staphylococcus aureus on inanimate surfaces
 |
When the prevalence of S. aureus on inanimate surfaces and among healthcare workers was compared, healthcare workers had a higher percentage (68.85%) than inanimate surfaces (45.69%).
The antibiotic susceptibility profile of S. aureus isolates is provided in Table 3. The isolates were more susceptible to meropenem, augmentin, tetracycline, ceftazidime, cefuroxime, and cephalexin. Of the 206 S. aureus isolates tested for MRSA using cefoxitin disk diffusion, 43.69% (n = 90) were methicillin-resistant (Table 4).
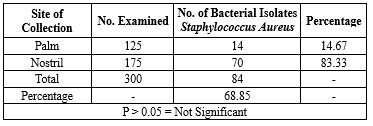


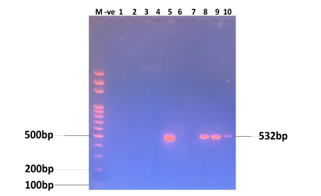 Figure 1. Agarose gel electrophoresis amplification of the mecA gene (532 bp) of S. aureus isolates. M, Marker (100 bp); lanes 1, 2, 3, 4, 6, and 7, negative; lanes 5, 8, 9, and 10, positive |
Discussion
S. aureus (45.69%) was the prevalent bacterium isolated from inanimate surfaces/fomites in this study. These results are comparable to those of the Brazilian study, which found that S. aureus was the primary organism isolated from fomites 53.3 percent of the time (25). The findings of Munveshyaka et al. (26) on inanimate surfaces and equipment are also consistent with these findings. S. aureus can form biofilms on inanimate surfaces/fomites, and these biofilms can be more resistant to disinfectants and cleaning efforts, making them a more persistent source of infection.
S. aureus was observed more frequently in the nostrils than on the palms of the hands in this study, which corresponds to the findings of Pant and Sharma (27) and Junu et al. (28). This result is consistent with the notion that S. aureus most frequently colonizes the nostrils. Compared with nasal carriers, there are fewer reports of hand carriers. Compared with Mukhiya et al. (29) and Pant and Sharma (27), the prevalence of palm-of-hand carriers was lower, which may suggest that the healthcare workers who took part in this study practiced better hand hygiene. In this investigation, every hand carrier was also a nasal carrier, and the isolates from both locations shared similar antibiograms, indicating that they were phenotypically identical. The notion that hands are the primary vector for spreading S. aureus from surfaces to the nostrils and from the nostrils to surfaces is further supported by the possibility that these carriers tend to pick their noses.
The bacterial isolates were resistant to frequently used antibiotics. Erythromycin (29.13%), cotrimoxazole (29.13%), gentamicin (33.98%), ampicillin (33.98%), and ciprofloxacin (36.41%) had low susceptibility rates against S. aureus. S. aureus was more resistant to these drugs. This could be due to their availability, cost, and misuse. This is in line with the findings of Sanusi et al. (30). Adam et al. (31), on the other hand, found that the highest rate of S. aureus resistance was to trimethoprim-sulfamethoxazole. This could be due to the development of resistance mechanisms such as reduced antibiotic accumulation within the bacteria and bypassing the antibiotic's inhibitory effects.
Of the 390 bacterial isolates obtained from the two tertiary hospitals in Abia State, 206 (52.82%) were positive for S. aureus. Mukhiya et al. (32) and Firesbhat et al. (33) reported the presence of S. aureus on hospital surfaces in Nepal and Ethiopia, respectively, despite the scarcity of data regarding the prevalence of MRSA in Nigeria. These results contradict those of this investigation. The findings of this study are in line with those of Anyadoh et al. (34) and Sanusi et al. (30), who found that more than 50% of hospital surfaces were contaminated with S. aureus.
The rise of MRSA, which is resistant to cephalosporins, a class of antibiotics commonly used to treat Staphylococcus infections, as well as monobactams and all beta-lactam drugs, has worsened the emergence of S. aureus infections (35). Identifying MRSA accurately requires prompt and early diagnosis because MRSA infections lead to treatment issues and spread (36).
In this study, 90 (43.69%) S. aureus isolates were found to be resistant by the cefoxitin disk diffusion test for MRSA. This is comparable to the study by Khairullah et al. (37), which revealed that 47.62% of the isolates tested positive for MRSA. In comparison, Adam et al. (31) and Oguzkaya-Artan et al. (38) reported 2.1% of MRSA positivity, while Sanusi et al. (30) reported 5.4%. According to this study, a number of variables, such as improper hand hygiene and failure to clean surfaces, might contribute to the development of MRSA contamination on fomites/inanimate surfaces and healthcare personnel. MRSA contamination raises the possibility of the spread of hard-to-treat Staphylococci, posing a major public health danger.
According to Miragaia (39), mecA genotyping by PCR remains the primary recommendation despite its inability to be carried out on a regular basis, and phenotypic detection of MRSA via disk diffusion has not yet yielded fully reliable results. Nevertheless, because of its speed and affordability, disk diffusion identification of MRSA is still often utilized (40).
Oxacillin and cefoxitin diffusion disks exhibit the same 100% sensitivity and 74.07% and 92.59% specificities, respectively (41). However, because there is still a high percentage of false positives with the oxacillin disk diffusion approach, a number of earlier investigations found that cefoxitin disk diffusion had a higher sensitivity level than oxacillin for identifying MRSA (42). According to Vyas et al. (41), beta-lactamase hyperproduction may contribute to false positives by causing oxacillin resistance to manifest phenotypically without a genotypic resistance mechanism.
A total of 20 suspected methicillin-resistant S. aureus isolates were tested for the mecA gene, and only 4 isolates (20% of all isolates tested by PCR) were mecA gene-positive. This might be due to false positives in the phenotypic analysis. Suspected MRSA isolates were found to have the mecA gene, as shown by the PCR results. This is similar to Khirullah et al. (37), where 30% of the MRSA isolates tested were mecA gene-positive. However, this contrasts with Sanusi et al. (30), who reported that 83.33% of MRSA isolates were positive for the mecA gene. These findings are in line with the study by Ramandinianto et al. (43). Because it can increase the expression of PBP2a, which the mecA gene encodes, cefoxitin is an effective inducer of mecA gene expression (44). This also agrees with Reichmann and Pinho (45).
Conclusion
This study was conducted to detect the mecA gene and MRSA from S. aureus isolated from inanimate surfaces, palms of the hands, and nostrils of healthcare workers in selected hospital wards in the two tertiary hospitals in Abia State. This study found an MRSA prevalence of 43.69% and mecA gene positivity of only 20%.
The hospital wards evaluated in this study showed the presence of bacterial pathogens on inanimate surfaces and in the nostrils of healthcare workers, with S. aureus being the prevalent bacterial isolate in this study. Nasal carriage was higher than hand carriage in this study.
The presence of MRSA in the two tertiary hospitals poses a risk to healthcare and community environments by contaminating healthcare workers, patients, visitors, and surrounding surfaces. This could ultimately lead to community exposure to resistant bacteria. Therefore, prevention and control measures are required to stop the spread of S. aureus infections on fomites/inanimate surfaces and among healthcare personnel at tertiary hospitals in Abia State.
However, the unavailability of molecular laboratories in close proximity to run the mecA gene analysis immediately limited this study.
Acknowledgement
We thank the management of the Federal Medical Centre, Umuahia, and the Abia State University Teaching Hospital, Aba, Abia State, for granting ethical approval. We are grateful to the healthcare workers who participated in this study for their informed consent. We also acknowledge Sir and Lady O. Mgbeokwere for their financial support.
Funding Sources
Not applicable.
Ethical Statement
The ethics committees of the Federal Medical Centre, Umuahia (Code: FMC/QEH/G.596/Vol.10/746), and Abia State University Teaching Hospital (Code: ABSUTH/MAC/117/VOL1/60) approved the study.
Conflicts of Interest
The authors have no competing interests.
Author Contributions
EUO: Conceptualization; Methodology; Data curation; Formal analysis; Funding acquisition; Investigation; Resources; Visualization; Writing-Original draft; Writing-Review and Editing. IO: Supervision; Methodology. EON: Methodology; Investigation; Interpretation.
Data Availability Statement
All data are available upon request from the corresponding author.
Use of Artificial Intelligence
The authors declare that no artificial intelligence tools were used in this work.
Research Article: Research Article |
Subject:
Microbiology
Received: 2025/03/21 | Accepted: 2025/10/28 | Published: 2026/04/25 | ePublished: 2026/04/25
Received: 2025/03/21 | Accepted: 2025/10/28 | Published: 2026/04/25 | ePublished: 2026/04/25
References
1. Amazian K, Rossello J, Castella A, Sekkat S, Terzaki S, Dhidah L. Prevalence of nosocomial infections in 27 hospitals in the Mediterranean region. East Mediterr Health J. 2010;16(10):1070-8. [View at Publisher] [DOI] [PMID] [Google Scholar]
2. World Health Organization. WHO guidelines on hand hygiene in health care: First global patient safety challenge clean care is safer care [homepage on the Internet]. Geneva: World Health Organization; 2009. Available from: https://www.ncbi.nlm.nih.gov/books/NBK144013. [View at Publisher]
3. Vincent J-L, Rello J, Marshall J, Silva E, Anzueto A, Martin CD. International study of the prevalence and outcomes of infection in intensive care units. JAMA. 2009;302(21):2323-9 [View at Publisher] [DOI] [PMID] [Google Scholar]
4. Lalami AEO, Touijer H, El-Akha F, Ettayebi M, Benchemsi N, Maniar S, et al. Microbiological monitoring of environment surfaces in a hospital in Fez city,Morocco. J Mater Environ Sci. 2016; 7(1):123-30. [View at Publisher] [Google Scholar]
5. Galvin S, Dolan A, Cahill O, Daniels S, Humphreys H. Microbial monitoring of the hospital environment: why and how? J Hosp Infect. 2012;82(3):143-151, [View at Publisher] [DOI] [PMID] [Google Scholar]
6. Huslage K, Rutala WA, Sickbert-Bennett E, Weber DJ. A quantitative approach to defining "high-touch" surfaces in hospitals. Infect Control hosp epidemiol. 2010;31(8):850-3. [View at Publisher] [DOI] [PMID] [Google Scholar]
7. Beggs C, Knibbs LD, Johnson GR, Morawska L. Environmental contamination and hospital-acquired infection: Factors that are easily overlooked. Indoor Air. 2015;25(5):462-74. [View at Publisher] [DOI] [PMID] [Google Scholar]
8. Martinez JA, Ruthazer R, Hansjosten K, Barefoot L, Snydman DR. Role of environmental contamination as a risk factor for acquisition of vancomycin-resistant enterococci in patients treated in a medical intensive care unit. Arch Intern Med. 2003;163(16):1905-12. [View at Publisher] [DOI] [PMID] [Google Scholar]
9. Ray AJ, Hoyen CK, Taub TF, Eckstein EC, Donskey CJ. Nosocomial transmission of vancomycin-resistant enterococci from surface. JAMA. 2002;287(11):1400-1. [View at Publisher] [DOI] [PMID] [Google Scholar]
10. Jabłońska-Trypuć A, Makuła M, Włodarczyk-Makuła M, Wołejko E, Wydro U, Serra-Majem L, et al. Inanimate Surfaces as a Source of Hospital Infections Caused by Fungi, Bacteria and Viruses with Particular Emphasis on SARS-CoV-2. Int J Environ Res Public Health. 2022;19(13):8121. [View at Publisher] [DOI] [PMID] [Google Scholar]
11. Lin D, Ou Q, Lin J, Peng Y, Yao Z. A meta-analysis of the rates of Staphylococcus aureus and methicillin-resistant S aureus contamination on the surfaces of environmental objects that health care workers frequently touch. Am J Infect Control. 2017;45(4):421-9. [View at Publisher] [DOI] [PMID] [Google Scholar]
12. O'Hara LM, Calfee DP, Miller LG, Pineles L, Magder LS, Johnson JK, et al. Optimizing Contact Precautions to Curb the Spread of Antibiotic-Resistant Bacteria in Hospitals: A Multicenter Cohort Study to Identify Patient Characteristics and Healthcare Personnel Interactions Associated with Transmission of Methicillin-Resistant Staphylococcus aureus. Clin Infect Dis. 2019;69(Suppl 3):S171-S7. [View at Publisher] [DOI] [PMID] [Google Scholar]
13. Cimolai N. MRSA and the Environment: Implications for Comprehensive Control Measures. Eur J Clin Microbiol Infect Dis. 2008;27(7):481-93. [View at Publisher] [DOI] [PMID] [Google Scholar]
14. Hardy KJ, Oppenheim BA, Gossain S, Gao F, Hawkey PM. A study of the relationship between environmental contamination with methicillin-resistant Staphylococcus aureus (MRSA) and patients' acquisition of MRSA. Infect Control Hosp Epidemiol. 2006;27(2):127-32. [View at Publisher] [DOI] [PMID] [Google Scholar]
15. Aldeyab MA, McElnay JC, Elshibly SM, Hughes CM, McDowell DA, McMahon MAS, et al. Evaluation of the Efficacy of a Conventional Cleaning Regimen in Removing Methicillin-Resistant Staphylococcus aureus from Contaminated Surfaces in an Intensive Care Unit. Infect Control Hosp Epidemiol. 2009;30(3):304-6. [View at Publisher] [DOI] [PMID] [Google Scholar]
16. Chaibenjawong P, Foster SJ. Desiccation Tolerance in Staphylococcus aureus. Arch microbiol. 2011;193(2):125-35. [View at Publisher] [DOI] [PMID] [Google Scholar]
17. Davis MF, Iverson SA, Baron P, Vasse A, Silbergeld EK, Lautenbach E, et al. Household transmission of meticillin-resistant Staphylococcus aureus and other staphylococci. Lancet Infect Dis. 2012;12(9):703-16. [View at Publisher] [DOI] [PMID] [Google Scholar]
18. Dietze B, Rath A, Wendt C, Martiny H. Survival of MRSA on sterile goods packaging. J Hosp Infect. 2001;49(4):255-61. [View at Publisher] [DOI] [PMID] [Google Scholar]
19. Domon H, Uehara Y, Oda M, Seo H, Kubota N, Terao Y. Poor Survival of Methicillin-Resistant Staphylococcus aureus on Inanimate Objects in the Public Spaces. Microbiologyopen. 2016;5(1):39-46. [View at Publisher] [DOI] [PMID] [Google Scholar]
20. Cheesbrough M. District Laboratory Practice in Tropical Countries, Part 2, 2nd edition, Cambridge University Press Publication, South Africa,, 2006. p.143-57. [View at Publisher] [DOI] [Google Scholar]
21. CLSI. Performance standards for antimicrobial susceptibility testing. 21st informational supplement. CLSI document M100-S21. Wayne (PA): Clinical and Laboratory Standards Institute; 2011. [View at Publisher]
22. Jorgensen JH, Turnidge JD. Susceptibility test methods dilution and disk diffusion methods. Manual of clinical microbiology, 9th Ed, ASM press 2007.p 1152-72. [View at Publisher] [DOI] [Google Scholar]
23. CLSI. Performance standards for antimicrobial susceptibility testing. 30th ed. CLSI supplement M100-S30. Wayne (PA): Clinical and Laboratory Standards Institute; 2020. [View at Publisher]
24. Wielders CL, Fluit AC, Brisse S, Verhoef J, Schmitz FJ. MecA gene is widely disseminated in Staphylococcus aureus population. J Clin Microbiol. 2002;40(11):3970-5. [View at Publisher] [DOI] [PMID] [Google Scholar]
25. Rodrigues DO, Peixoto LDP, Barros ETM, Guimarães JR, Gontijo BC, Almeida JL, et al. Epidemiology of bacterial contamination of inert hospital surfaces and equipment in critical and non-critical care units: a Brazilian multicenter study. Microbiol Res J Int. 2020;30(7):302–7. [View at Publisher] [DOI] [Google Scholar]
26. Munveshyaka E, Cyuzuzo P, Yadufashije C, Karemera J. Contribution of Medical Wards Contamination to Wound Infection among Patients Attending Ruhengeri Referral Hospital. Int J Microbiol. 2021:2021:7838763. [View at Publisher] [DOI] [PMID] [Google Scholar]
27. Pant ND, Sharma M. Carriage of methicillin resistant Staphylococcus aureus and awareness of infection control among healthcare workers working in Intensive care unit of a hospital in Nepal. Braz J Infect Dis. 2016;20(2):218-9. [View at Publisher] [DOI] [PMID] [Google Scholar]
28. Junu JR, Amatya R, Rai SK. Hand and nasal carriage of Staphylococcus aureus and its rate of recolonization among healthcare workers of a tertiary care hospital in Nepal. JAC Antimicrob Resist. 2022;4(3):dlac051. [View at Publisher] [DOI] [PMID] [Google Scholar]
29. Mukhiya RK, Shrestha A, Rai SK. Prevalence of Methicillin resistant Staphylococcus aureus in hospitals of Kathmandu Valley, Nepal. J sci technol. 2012;13(2):185-90. [View at Publisher] [DOI] [Google Scholar]
30. Sanusi AA, Dangari MA, Salihu MK, Ado A. Molecular detection of mecAgene in Methicillin resistant Staphylococcus aureus isolated from surfaces of some public hospitals in Katsina state, Nigeria. UMYU J Microbiol Res. 2023;8(2):110-7. [View at Publisher] [DOI] [Google Scholar]
31. Adam AS, Lisa M, Sarah KO, Ntulume I, Aliero AA, Namatovu A. Antibiotic Susceptibility Pattern and Detection of mecA Gene in Methicillin resistant Staphylococcus epidermidis Isolated from Wards Surfaces of Kampala International University Teaching Hospital, Uganda. Romanian Arch Microbiol Immunology. 2020;79(1):24-36. [View at Publisher] [Google Scholar]
32. Mukhiya RK, Shrestha A, Rai SK, Panta K, Singh RN, Rai G, et al . Prevalence of Methicillin-Resistant Staphylococcus aureus in Hospitals of Kathmandu Valley. Nepal J Sci Technol. 2012;13(2):185-90. [View at Publisher] [DOI] [Google Scholar]
33. Firesbhat A, Tigabu A, Tegene B, Gelaw B. Bacterial profile of high-touch surfaces, leftover drugs and antiseptics together with their antimicrobial susceptibility patterns at University of Gondar Comprehensive Specialized Hospital, Northwest Ethiopia. BMC Microbiol. 2021;21(1):309. [View at Publisher] [DOI] [PMID] [Google Scholar]
34. Anyadoh-Nwadike SO, Eri O, Nwaokoro JC, Nwadike PO. Prevalence of Staphylococcus aureus within the Hospital Environment. Asian J Med Pharm Res. 2011;1(1):17-21. [View at Publisher] [Google Scholar]
35. Bush K, Bradford PA. Β-Lactams and β-Lactamase Inhibitors: An Overview. Cold Spring Harb Perspect Med. 2016;6(8):a025247. [View at Publisher] [DOI] [PMID] [Google Scholar]
36. Mehta Y, Hegde A, Pande R, Zirpe KG, Gupta V, Ahdal J, et al. Methicillin-resistant Staphylococcus aureus in Intensive Care Unit Setting of India: A Review of Clinical Burden, Patterns of Prevalence, Preventive Measures, and Future Strategies. Indian J Crit Care Med. 2020;24(1):55-62. [View at Publisher] [DOI] [PMID] [Google Scholar]
37. Rafif Khairullah A, Rehman S, Agus Sudjarwo S, Helmi Effendi M, Chasyer Ramandinianto S, Aega Gololodo M, et al. Detection of mecA gene and methicillin-resistant Staphylococcus aureus (MRSA) isolated from milk and risk factors from farms in Probolinggo, Indonesia. F1000Res. 2022;11:722. [View at Publisher] [DOI] [PMID] [Google Scholar]
38. Oguzkaya-Artan M, Baykan Z, Artan C, Avsarogullari L. Prevalence and risk factors for methicillin resistant Staphylococcus aureus carriage among emergency department workers and bacterial contamination on touch surfaces in Erciyes University Hospital, Kayseri, Turkey. Afr Health Sci. 2015;15(4):1289-94. [View at Publisher] [DOI] [PMID] [Google Scholar]
39. Miragaia M. Factors contributing to the Evolution of mecA-Mediated β-lactam Resistance in Staphylococci: Update and New Insights from Whole Genome Sequencing (WGS). Front microbiol. 2018;9:2723. [View at Publisher] [DOI] [PMID] [Google Scholar]
40. Bennett K, Sharp SE. Rapid differentiation of methicillin-resistant Staphylococcus aureus and methicillin-susceptible Staphylococcus aureus from blood cultures by use of a direct cefoxitin disk diffusion test. J Clin Microbiol. 2008;46(11):3836-8. [View at Publisher] [DOI] [PMID] [Google Scholar]
41. Vyas A, Sharma M, Kumar S, Kumar M, Mehra SK. A comparative study of Oxacillin screen agar, Oxacillin disk diffusion and Cefoxitin disk diffusion, Oxacillin E-test method for routine screening of methicillin-resistant Staphylococcus aureus. Int J Curr Res Rev. 2015;7(10):55-60. [View at Publisher]
42. Broekema NM, Van TT, Monson TA, Marshall SA, Warshauer DM. Comparison of Cefoxitin and Oxacillin Disk Diffusion Methods for Detection of mecA-Mediated Resistance in Staphylococcus aureus in a Large-Scale Study. J Clin Microbiol. 2009;47(1):217-9. [View at Publisher] [DOI] [PMID] [Google Scholar]
43. Ramandinianto SC, Khairullah AR, Effendi MH. MecA gene and methicillin-resistant Staphylococcus aureus (MRSA) isolated from dairy farms in East Java, Indonesia. Biodiversitas. 2020;21(8):3562-8. [View at Publisher] [DOI] [Google Scholar]
44. Koupahi H, Jahromy SH, Rahbar M. Evaluation of Different Phenotypic and Genotypic Methods for Detection of Methicillin Resistant Staphylococcus aureus (MRSA). Iran J Pathol. 2016;11(4):370-6. [View at Publisher] [PMID] [Google Scholar]
45. Reichmann NT, Pinho MG. Role of SCC mec type in resistance to the synergistic activity of oxacillin and cefoxitin in MRSA. Sci Rep. 2017;7(1):6154. [View at Publisher] [DOI] [PMID] [Google Scholar]
Send email to the article author
| Rights and permissions | |
 |
This work is licensed under a Creative Commons Attribution-NonCommercial 4.0 International License. |

This work is licensed under a Creative Commons Attribution-NonCommercial 4.0 International License.
Contact us
Tel & Fax: (+98) 17-32450093
E-mail:
 goums.ac.ir
 yahoo.com